▎Tesamoreli Research
Molecular Background
Tesamoreli (TH9507) is a synthetic 44-amino-acid analogue of human growth hormone-releasing hormone (GHRH). A trans-3-hexenoyl group is attached to the N-terminal tyrosine residue, a modification developed to increase resistance to enzymatic degradation. PubChem lists Tesamoreli under CID 16137828, with the molecular formula C221H366N72O67S and a molecular weight of approximately 5136 g/mol.[7,8]
Research Progress
Eckhardt S. Ferdinandi and colleagues evaluated TH9507 in pigs, rats, and dogs using repeated intravenous or subcutaneous exposure at study doses up to 600 μg/kg. The investigators measured growth hormone (GH), insulin-like growth factor-1 (IGF-1), toxicokinetic parameters, body weight, clinical chemistry, hematology, and organ-related findings. They reported increased GH and IGF-1 responses across the animal models and dose-related exposure to immunoreactive TH9507. In subchronic studies lasting up to 4 months, reversible liver, kidney, hematologic, clinical-chemistry, and organ-weight changes were more evident in dogs and were interpreted by the authors in the context of prolonged exposure to supraphysiological GH and/or IGF-1. The apparent elimination half-life reported in dogs ranged from 21 to 45 minutes.[2]
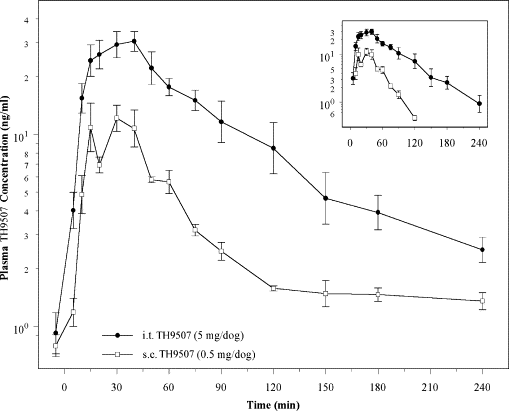
Mendel Jansen and colleagues studied TH9507 pharmacokinetics in male beagle dogs after intratracheal dry-powder administration and subcutaneous exposure at approximately 375 μg/kg; a separate intravenous study was used to estimate absolute bioavailability. Plasma TH9507 was measured by radioimmunoassay. The authors reported relative bioavailability of approximately 41% for the intratracheal route compared with subcutaneous administration and an estimated absolute bioavailability of approximately 13%. Terminal half-life values were similar between intratracheal and subcutaneous administration, while mean residence time was longer after intratracheal delivery under the study conditions.[3]
![Fig1]()
Fig1. Plasma TH9507 concentrations reported after intratracheal and subcutaneous administration in beagle dogs.[3]
The source figure presents geometric mean plasma TH9507 concentrations over time, including values after correction for baseline assay interference. Dose, group size, analytical method, and complete pharmacokinetic procedures are reported in the original publication.[3]
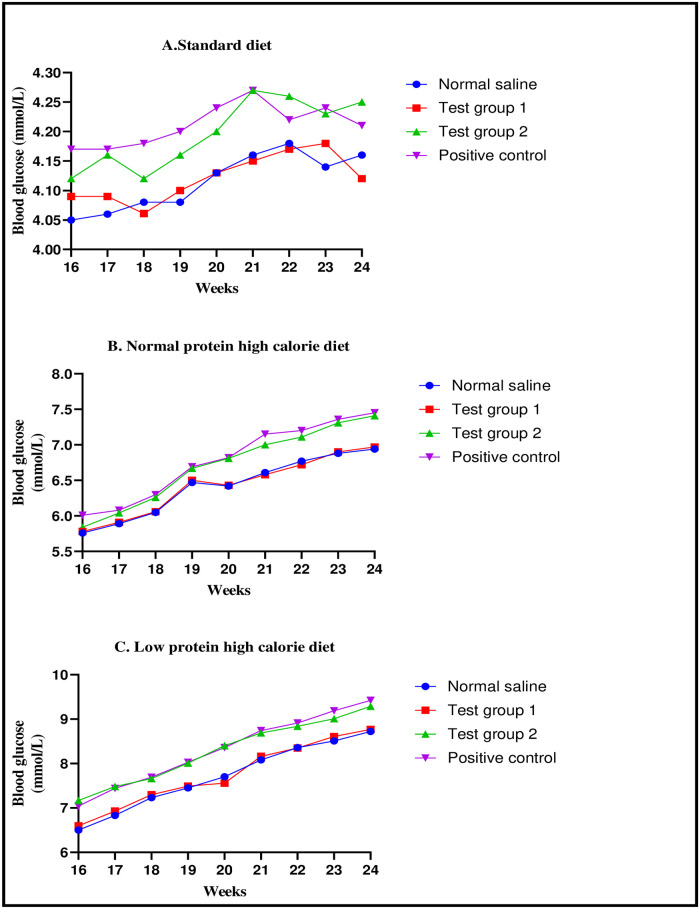
Boniface M. Chege and colleagues randomized 120 newly weaned Sprague-Dawley rats to standard, low-protein high-calorie (LPHC), or normal-protein high-calorie (NPHC) diets for 15 weeks and then subdivided each dietary group into four treatment groups for a further 9 weeks: saline control, TDF + 3TC + DTG with tesamorelin, TDF + 3TC + DTG without tesamorelin, or AZT + 3TC + ATV/r. The authors evaluated body weight, fasting blood glucose, oral glucose tolerance, plasma lipids, liver weight, hepatic triglycerides, adiposity, insulin, and GH. In the NPHC and LPHC groups, the tesamorelin-free TDF + 3TC + DTG group and the classical cART group showed increases in several metabolic measurements and lower GH concentrations. The authors reported that co-administration of tesamorelin with the TDF + 3TC + DTG regimen was associated with different metabolic measurements compared with the same cART regimen without tesamorelin. Because tesamorelin was studied only as part of a combination regimen, the study does not isolate its independent effect.[4]
![Fig2]()
Fig2. Weekly fasting-blood-glucose measurements during the treatment phase of the cited rat study.[4]
The source figure compares the four treatment groups within the standard, normal-protein high-calorie, and low-protein high-calorie dietary conditions. Group definitions, statistical comparisons, and complete study procedures are reported in the original publication.[4]
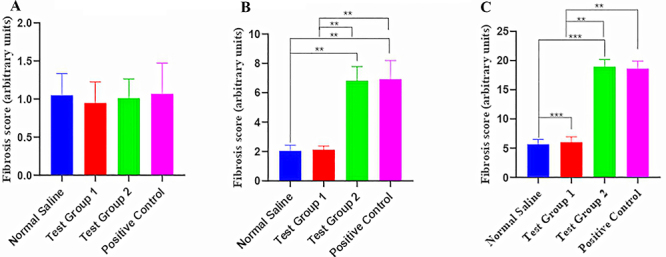
In a related study, Boniface M. Chege and colleagues used the same three dietary conditions and four treatment-group framework to examine electrocardiographic and myocardial histology outcomes in rats. The investigators reported significant intergroup differences in several ECG measurements. Myocardial fibrosis was reported in animals receiving the tesamorelin-free DTG-based regimen and the classical cART regimen under the calorie-dense dietary conditions, while the group receiving DTG together with tesamorelin showed a different histological pattern. The authors interpreted these findings as evidence that the diet and antiretroviral regimen influenced the cardiac phenotype and that tesamorelin co-treatment modified the response. Because the study used a combination regimen, the independent contribution of tesamorelin cannot be separated from treatment interactions.[5]
![Fig3]()
Fig3. Left-ventricular fibrosis measurements reported across the dietary and antiretroviral treatment groups in the cited rat study.[5]
The source figure compares fibrosis scores in the saline, DTG + tesamorelin, DTG-only, and classical cART groups under normal-chow, calorie-dense normal-protein, and calorie-dense low-protein diets. Statistical comparisons and complete experimental conditions are reported in the original publication.[5]
Andre Knoop and colleagues developed an immunoaffinity purification and nano-UHPLC-HRMS/MS method for identifying several GHRH analogues and related metabolites in plasma, including Geref (Sermorelin), CJC-1293, CJC-1295, and Egrifta-associated Tesamoreli. The method was evaluated for specificity, linearity, recovery, detection limits, imprecision, and matrix effects. In animal experiments, the parent compounds were detectable for at least several hours after administration, while the expected metabolites were not identified in the rodent samples. The study primarily addressed analytical detection for anti-doping applications and did not evaluate the biological efficacy or safety of a Tesamoreli research material.[6]
Research Limitations
The studies summarized above use different experimental systems and answer different research questions, including nonclinical toxicology, canine pharmacokinetics, antiretroviral combination studies in rats, and analytical mass-spectrometry detection. Results from these systems are not directly interchangeable. In the Chege studies, tesamorelin was administered together with a TDF + 3TC + DTG regimen; therefore, comparisons can describe differences between combination groups but cannot fully separate the independent contribution of tesamorelin or exclude interactions with antiretroviral treatment.[4,5]
Tesamoreli is also the proper name of the active peptide in FDA-approved EGRIFTA SV and EGRIFTA WR biological products. FDA describes tesamorelin as a synthetic 44-amino-acid human GHRF analogue with an N-terminal hexenoyl modification and lists the approved EGRIFTA formulations under BLA 022505.[8,9] Those approvals apply to the specific licensed products, formulations, manufacturing controls, strengths, and labeled use. They do not establish FDA approval, equivalence, safety, or efficacy for an independently supplied COCER Peptides research material.
COCER Peptides presents Tesamoreli solely for laboratory research and analytical use. It is not intended for human or veterinary use. This COCER Peptides material is not EGRIFTA SV or EGRIFTA WR and is not an FDA-approved drug or biological product. The research described above summarizes findings reported in third-party publications and is not a statement of clinical efficacy, safety, diagnosis, treatment, prevention, or an instruction for use.